Acls Precourse Self Assessment Questions And Answers
So, you’re staring at the ACLS Precourse Self-Assessment, and your brain is already doing that thing where it forgets the difference between asystole and a bad burrito. Welcom...

So, you’re staring at the ACLS Precourse Self-Assessment, and your brain is already doing that thing where it forgets the difference between asystole and a bad burrito. Welcome to the club. This is the hazing ritual for anyone who wants to save a life while looking slightly less panicked than the patient. The questions are designed to make you feel like a genius one minute and a paramedic who just plugged the defibrillator into the wall outlet the next.
Let’s be real: the material is terrifying, but the test is just a warm-up. It’s the MCAT for chest compressions, but with more beeping and fewer kale smoothies. The goal isn’t to break you; it’s to remind you that pulseless electrical activity (PEA) is not a new indie band. You’ll see questions about when to push epinephrine, and your first instinct might be to guess “when the patient is being grumpy.” Shockingly, that’s not in the textbook.
The Rhythm Game: You Will See Weird Squiggles
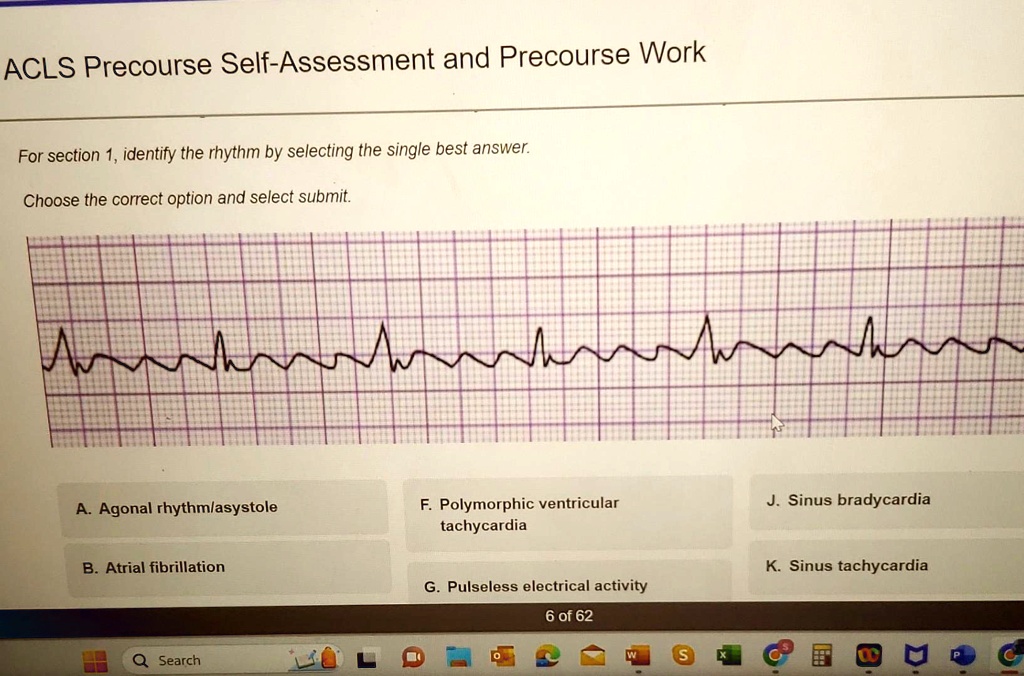
The self-assessment loves showing you those squiggly lines that look like a toddler having a seizure on an EKG monitor. You’re supposed to identify ventricular tachycardia, but your brain will scream, “It’s the one that goes up and down!” Spoiler alert: they are all up and down.
Must Read
Here’s a surprising fact: up to 80% of people mess up the first time they try to identify Torsades de Pointes, mostly because they’re too busy laughing at the name. It sounds like a dessert in a French bakery, but if you order it, the waiter brings a crash cart. The trick is to remember that chaotic rhythm means you grab the magnesium, not the crème brûlée.
One question will inevitably ask about synchronized cardioversion vs. defibrillation. Imagine the difference between gently convincing a drunk friend to sit down (synchronized) versus tackling them through a window (defibrillation). Both work, but one leaves the furniture intact.
The Drug Cocktail: Epinephrine is Your BFF
You will be asked about epinephrine approximately 47 times. The answer is almost always 1 mg every 3-5 minutes. If you forget, just picture a tiny, screaming person inside a heart shouting, “AGAIN!” That’s basically the chemical mechanism.
Amiodarone is the cool cousin who shows up late to the party but saves the day. The test loves asking about its dose: 300 mg first, then 150 mg. If you mix this up with the epinephrine dose, you’ll either zap the patient’s rhythm or give them a panic attack that revives them out of sheer annoyance.
Here’s a jaw-dropper: Vasopressin was kicked off the ACLS algorithm in 2015. It’s like the B-list actor who was written out of the show. If you see it in an answer choice, laugh and move on. It’s a ghost drug now, haunting the margins of old flashcards.
 Texts acls precourse self assessment and precourse work for...
The Shocking Truth About “No Shock Advised”
One of the most confusing parts is when the defibrillator yells, “No shock advised” and you’re standing there with paddles in hand like a confused electrician. The answer is always resume CPR immediately. The machine is, ironically, smarter than you in that moment.
I once saw a student argue with the AED. “But the guy is flatlining!” he yelled. The instructor calmly said, “That’s PEA. Shocking it is like throwing a hair dryer into a swimming pool full of Jell-O. It doesn’t work.” That moment has haunted me ever since, so I pass it on to you.
There will be a question about post-cardiac arrest care. The correct answer usually involves “targeted temperature management.” That’s fancy talk for ice packs in the armpits to stop the brain from melting into soup. Science is weird and wonderful.
The Breathing Trap: “But He’s Still Gasping!”
Ah, agonal breathing. It sounds like a dying walrus on a foggy beach. The test will ask if you give breaths. The answer is yes, because gasping is not breathing—it’s the body trying to sneeze the soul back in. Don’t be fooled by the drama.
A shocking statistic: only about 10% of people survive cardiac arrest outside a hospital. That makes the self-assessment feel less annoying, doesn’t it? It’s not a pop quiz; it’s a game of “Don’t let your friend be that 90%.” No pressure, though.
 Alcohol Pre-Test Sa-1 Answers at Eileen Porras blog
The test will also question your morality with a scenario about a “do not resuscitate” bracelet. The correct answer is: do not shock the grandpa. Even if he looks like he’s just taking a nap at a heavy metal concert.
Multiple Choice Madness: The “Best” vs. “Next” Trap
The assessment loves asking for the “best” action versus the “next” action. It’s a semantic torture rack. The trick is to prioritize circulation over everything. The heart is a muscle that can get grumpy—push hard, push fast, and let the algorithms sort out the paperwork.
One question will ask, “What is the preferred site for IO access?” and your brain will say, “The bone? Are we serious?” Yes. You drill into the shin like you’re building IKEA furniture for a dying man. It works. It’s blood magic.
Let’s be real: you will get some wrong. The pass threshold is often 84%, which means you can miss a few while still being a hero. If you fail, you just retake it. It’s like a video game where the penalty is mildly injured pride and reading the manual again.
Finally, the best strategy for the Precourse Self-Assessment is to embrace the chaos. Laugh at the bizarre rhythms. Mock the lengths of the drug names. Then, when you ace it, remember: you’ve just proven you can handle a false alarm. The real heart attack will be easier. Probably. Just bring the epinephrine and a good attitude.
