American Academy Of Neurology Migraine Guidelines
Okay, let’s talk about that thing that makes you want to live in a dark, quiet cave with a cold compress on your face. You know what I mean: migraines. They are the absolute w...

Okay, let’s talk about that thing that makes you want to live in a dark, quiet cave with a cold compress on your face. You know what I mean: migraines. They are the absolute worst, like a tiny, angry gremlin decided to set up a jackhammer in your skull. But guess what? The American Academy of Neurology (AAN) just dropped some new guidelines, and they're basically a battle plan for that gremlin.
So, what did these super-smart neurologists actually say? First, they affirmed what many of us already suspect: migraine is not just a "bad headache." It's a legitimate neurological disorder. Take that, anyone who has ever told you to "just drink more water." The AAN is giving you a shiny, science-backed permission slip to take your pain seriously.
The Big News: Prevention Gets A Major Power-Up
For years, we’ve been told to just pop a pill when the pain hits. That’s like trying to put out a forest fire with a water pistol. The new guidelines scream: Prevention is key! They specifically highlight a few heavy hitters for stopping migraines before they even start.
Must Read
Let’s talk about the class of drugs called CGRP inhibitors, or as I call them, "gremlin-slayers." These are game-changers. They don’t just dull the pain; they block the whole party before the gremlin can set up the sound system. The AAN says these are highly effective for prevention, and honestly, it’s about time we had something that works better than an ice pack and a prayer.
But wait—they also gave a shout-out to the old faithfuls. Botox is still a rockstar for chronic migraine. Yes, Botox. The same stuff that makes people look surprised for months can also make you feel like a functional human. It’s weird, it’s wonderful, and now the AAN has officially given it the full stamp of approval.
What About The "Rescue" Plan?
You know those days when the gremlin shows up uninvited and you need it gone now? The AAN has thoughts on that, too. Their new guidelines point to a newer oral med called gepants (like ubrogepant and rimegepant). These are like the SWAT team of migraine drugs—fast, targeted, and less likely to make you feel like a zombie afterward.
 Virtual Resident Education Lecture Series: Pediatric Headache
They’re also giving a thumbs-up to lasmiditan, a novel drug that works differently than triptans. Triptans (like Imitrex) are great, but they can make some people feel like they’re having a heart attack. Lasmiditan is a nice alternative, though the AAN gently notes it might make you a little dizzy—so maybe don’t plan to drive a racecar right after taking it. Kidding… mostly.
And here’s a fun little plot twist: the guidelines are starting to embrace non-drug options more seriously. Things like neuromodulation devices (fancy gadgets that zap your nerves), cognitive behavioral therapy, and even acupuncture are getting a nod. Are they a cure-all? Nope. But the AAN says they’re solid evidence-based tools to have in your arsenal.
Let’s Talk About The Elephant In The Room: "But My Doctor Said…"
Have you ever had a doctor shrug and say, "There’s not much else we can do"? That’s the old-school, pre-2024 thinking. The new AAN guidelines are a direct message to every healthcare provider: Stop gatekeeping! They clearly recommend that if one treatment fails, you try another. And another. And another. There is no "one-size-fits-all" for migraines—and the AAN is finally spelling that out.
They also emphasize that lifestyle changes are not punishments. Getting enough sleep, eating regularly, and managing stress aren't just nice ideas—they are medical recommendations backed by data. Your gremlin hates a predictable routine. So annoy it by going to bed at the same time every night. Yes, even on weekends.
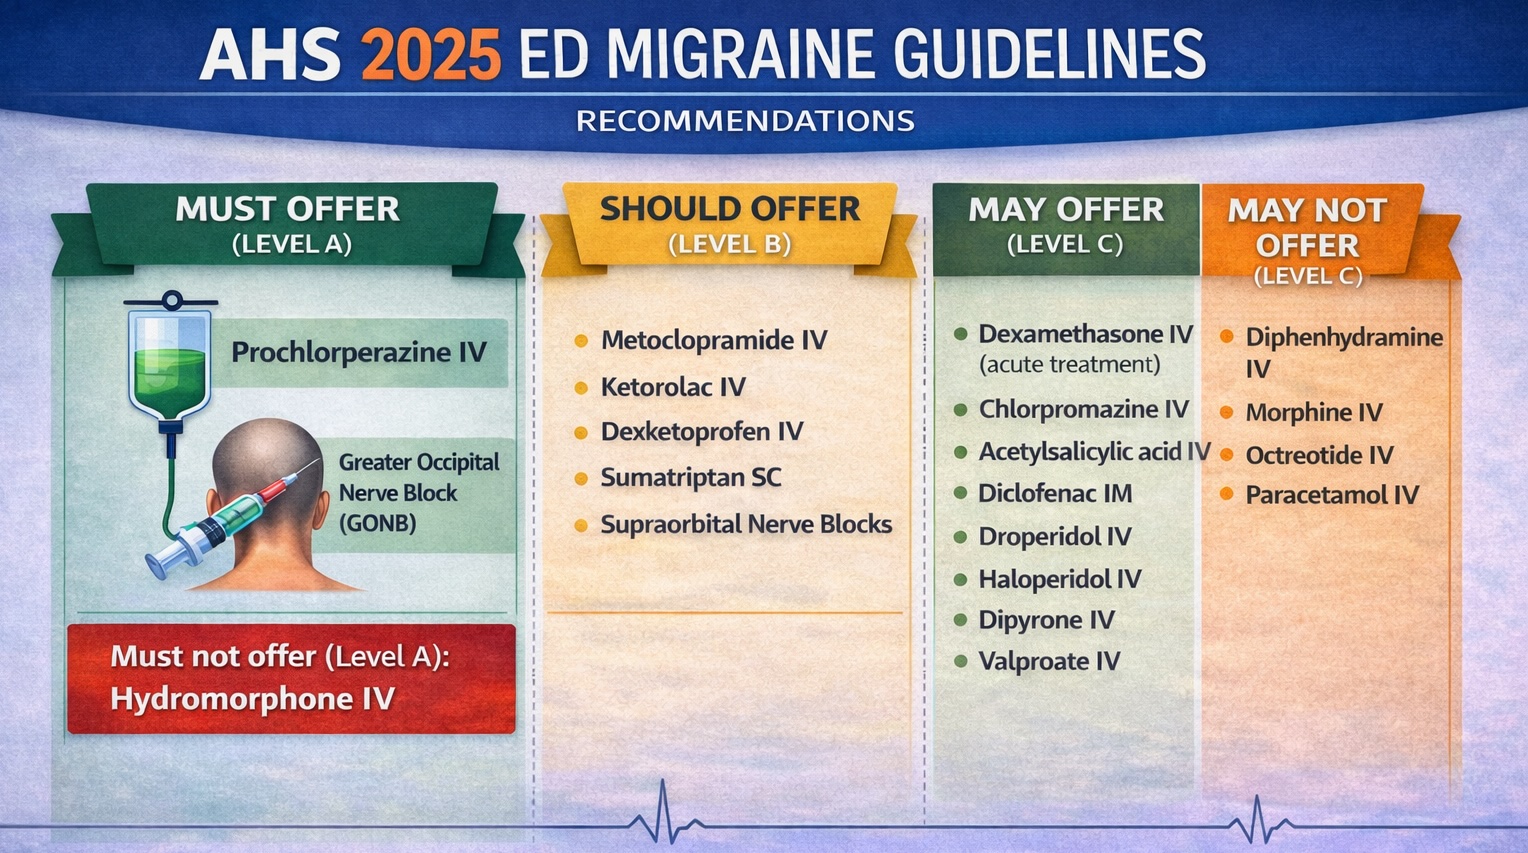 2025 AHS Guidelines for Parenteral Migraine Treatment in the ED
The "Take This Seriously" Rule
Here’s the part that made me actually cheer: the AAN now says that imaging tests (like MRIs) are not automatically needed for most people with migraine. That saves you a lot of anxiety and a huge bill. But they also warn that if your symptoms change suddenly—like a new kind of pain or a weird aura—you should absolutely get checked out. Trust your gut over Dr. Google.
And for all you ladies out there (because migraines love women, aka the patriarchy’s favorite target), the guidelines now have specific advice for hormonal triggers. The AAN says certain birth control methods can actually help prevent menstrual migraines. It’s not a silver bullet, but it’s a solid option to bring up with your gynecologist. See? We can talk about everything over coffee.
So, What’s The Takeaway?
You are not alone. You are not "weak." And you are not out of options. The American Academy of Neurology just handed you a new toolkit. It says: try the new drugs, don’t settle for the old ones, and keep a consistent sleep schedule even if it means leaving that party early. (Your gremlin will hate you for it, which is the whole point.)
Go ahead—call your neurologist. Show them this article if you have to. Say, "Hey, the AAN says I deserve better." Because you do. Now go drink some water, and maybe keep those CGRP inhibitors on speed dial. You’ve got this.
